
Savonne Torain
Heartbeat's Governing Essentials Checklist
Could your Board, Executive Director and organization benefit from Heartbeat’s Governing Essentials Consultation? Let’s find out.
Check all that apply.
If you checked 2 or more of the above, it’s time for a Heartbeat International board consultation expert to come alongside you. Reach out to us today! This email address is being protected from spambots. You need JavaScript enabled to view it.
Spiritual Spring Devotional
by Lauri Campbell, LAS, Affiliate Coordinator
See, I am doing a new thing! Now it springs up; do you not perceive it? I am making a way in the wilderness and streams in the wasteland. Isaiah 43:19
In February’s devotional, we discussed Navigating a Spiritual Winter. April seems like a great time to consider how we might approach a Spiritual Season of Spring, especially since many of us are fresh from the Conference in Cincinnati or the virtual Conference. New ideas abound!
When God takes us through a Spiritual Spring, it is a time to plant and implement the instructions we received from Him during a Spiritual Winter. He’s doing a new thing that requires our attention and action.
Now is the time to use the fresh, renewed sight He has given us and plant some things that will bear good fruit in our lives and for His Kingdom. The insight and rest we received from the winter season provides spiritual enthusiasm for the hard work of planting.
Has God refined your mission? Calling? Vision? Assignment?
Has your faith been strengthened to accomplish what He’s called you to do?
Has He given you a brand new assignment?
Maybe He simply realigned your heart with your assignment and there’s a holy confidence you lacked before.
Whatever it is, it’s new and God is doing it in and through you. But planting is where the work begins in many ways. It can take the form of training and education to prepare for the harvest of new fruit. It may look like enlisting a mentor to sharpen you professionally or spiritually for the work that lies ahead. A Spiritual Spring can yield new connections that require cultivation in order to steward them well.
The Bible teaches that the work you do now will determine your fruit in the future, so plant wisely. “Whoever sows sparingly will also reap sparingly, and whoever sows generously will also reap generously." (2 Corinthians 9:6).
The Scripture also makes this promise about sowing/planting:
“...because the one who sows to his flesh will reap corruption from the flesh, but the one who sows to the Spirit will reap eternal life from the Spirit. So we must not get tired of doing good, for we will reap at the proper time if we don’t give up.” Galatians 6:8-9
The Passion Translation says it this way:
“The harvest you reap reveals the seed that you planted. If you plant the corrupt seeds of self-life into this natural realm, you can expect a harvest of corruption. If you plant the good seeds of Spirit-life, you will reap beautiful fruits that grow from the everlasting life of the Spirit.” Galatians 6:8 TPT
With your new insight and renewed passion, God is calling you to plant spiritual seeds that will reap beautiful, everlasting fruit in your life. Spiritual fruit that will have a Kingdom impact on those around you.
So, do not grow weary in generously planting spiritual seeds that will bear Christ-honoring fruit. God has promised that you will reap what you sow in due season if you do not give up.
If Abortion Is the Answer… What Was the Question?
by Michele Cheresnick, LAS, Affiliate Coordinator
You’ve seen it before: a young woman walks in, scared and unsure, convinced abortion is her only choice. You know the questions behind her decision—fear, isolation, uncertainty—but also the moments where a listening ear, a calm voice, or a steady presence can change everything.
For those of you on the frontlines of the pregnancy help movement, you know that awareness alone doesn’t capture the full story. Understanding the fears and pressures that bring women to our doors allows us to respond with the wisdom, compassion, and support they need before crisis overwhelms them.
Abortion is often presented as a solution. A solution to fear. A solution to uncertainty. A solution to circumstances that feel impossible. And yet, every solution is connected to a problem.
So if abortion is the answer… What was the question?
For many of the women we serve, the question isn’t whether life is valuable. It’s whether they can survive the pressure, fear, and isolation that surround an unexpected pregnancy:
How can I be pregnant (again)?
What am I going to do?
I can’t do this by myself…
What if the father walks away?
What will my family say?
Can I survive the judgment, the cost, the disruption?
What does this mean for my future?
But we also have to be honest about the reality that comes before the pregnancy. Many women who have abortions are making choices in a moment of sexual activity where pregnancy was not a concern. They didn’t set out to create this situation—they weren’t thinking about a baby at the time. And that is where we have to start our conversations—before the after, before the crisis. It’s here, in the choices that precede pregnancy, that real awareness begins. Helping young people understand how their choices can shape the path of life and relationships before a crisis arises is not judgment—it’s preparation, care, and love.
We also have to recognize that male partners are often part of the decision—sometimes supportive, sometimes absent, sometimes unsure themselves. Their attitudes and willingness to step into responsibility can weigh heavily on the woman’s choices. This is an opportunity for us, as ministry leaders and advocates, to guide men toward accountability and care, so that support for life comes from both sides of the equation.
April is Abortion Recovery Awareness Month—a reminder that the work of pregnancy help doesn’t end with a birth or a choice. Many women continue to carry the emotional and spiritual weight of abortion long after the immediate decision. As ministry workers, you know the importance of walking with women not just through the pregnancy, but through the aftermath—providing healing, hope, and the support they need to reclaim life and move forward. Awareness isn’t just about statistics; it’s about understanding the whole journey, before and after, and being a presence of grace along the way.
Abortion has become a cultural shortcut, a quick fix to a deeper set of challenges. And that raises a hard question:
What does it say about our culture when the “solution” is to remove the smallest, most vulnerable person in the room?
Many of you have witnessed the reality behind the statistics firsthand. A young woman comes in convinced abortion is her only choice, not because she doesn’t value life, but because she feels alone. She might say, “I didn’t feel like I had a choice, I felt like I had to have an abortion.”
This is the reality we face daily in our ministries. Many women are not rejecting life; they are desperate for support. And it’s here, in these difficult moments, that our work matters most.
Abortion Awareness Month is a reminder that our mission goes beyond awareness—it’s about understanding the circumstances that make abortion feel inevitable.
Across the country, your ministries are already doing incredible work. Ultrasounds, parenting education, material resources, mentoring, and advocacy all make a difference. But the most radical act remains simple: being present. Listening. Walking with women long enough for them to see that life is never something they face alone.
Scripture reminds us that every life is intentionally formed (Psalm 139:13–14) and that we are called to “speak up for those who cannot speak for themselves” (Proverbs 31:8). Our calling is to translate awareness into action, both in the lives of the women we serve and the culture around us.
We are called to ask the deeper questions—and then to be part of the solution.
To walk with women. To meet fear with courage. To meet isolation with community. To meet uncertainty with hope. To guide towards choices that honor life before a crisis arises. To invite men into responsibility and care.
And in all of this, we want to take a moment to recognize you—the people on the frontlines. Your dedication, your patience, your willingness to show up in the hardest moments make an eternal difference. Thank you for the tireless, often unseen work you do every day to support women, children, and families. Your faithfulness is life-giving, and your impact is profound.
Love That Gives Life
by Jennifer Ellis, Manager of Academy
April ushers in two celebrations. It is Volunteer Appreciation Month, a time to pause and say thank you to those who give of themselves and their time and energy so faithfully. And it is the month we celebrate Easter, the sacrifice and resurrection of Jesus, the greatest act of love the world has ever known.
At first glance, these may seem like separate themes. But when we look more closely, they share a powerful core: sacrificial love that brings life.
Easter reminds us that love is not just a feeling. It is an action. It is costly. It is sacrificial.
Jesus willingly laid down His life so that we might live. His sacrifice was not accidental. It was not reluctant. It was not convenient. It was purposeful, voluntary, and motivated entirely by love. On Good Friday, it looked like loss and darkness. It looked like the end. But Sunday came, and resurrection followed sacrifice. Life followed surrender. Hope rose from what appeared to be defeat.
We see sacrifice that leads to life in pregnancy help every single day.
We see reflections of love every single day. Volunteers say “yes” again and again in ways that may not be dramatic but are deeply meaningful.
They say yes:
- After full workdays.
- On evenings when the couch is calling and rest would be easier.
- When family time competes for their attention.
- To paperwork, technology, phone calls, mentoring sessions, sorting donations, and sitting quietly across from a woman who is afraid and may not know what love looks or feels like.
Many volunteers serve while balancing careers, parenting, church commitments, and caring for aging parents. Some drive long distances. Some rearrange schedules. Some give financially in addition to their time. They carry stories home in their hearts and lift them up in prayer long after the office lights are turned off.
They are not called to give their lives on a cross, but they give something deeply personal. They give time, energy, emotional and spiritual presence, compassion, and so much more. In doing so, they make space for life.
In their faithful presence, an anxious mother finds courage.
In their listening ear, shame loosens its hold.
In their patient guidance, a baby is welcomed into the world.
In their quiet advocacy, an adoptive family is formed.
In their prayerful support, a woman discovers grace instead of judgment.
Much of this work happens behind the scenes, quietly. Sometimes, volunteers do not see the outcome of the seeds they plant. They may never know the full story of the life they helped protect or the generational impact of the hope they helped restore.
On Good Friday, it seemed as though the story had ended in loss. But what appeared as defeat was the turning point of history.
In ministry, we often exist in the space between Friday and Sunday. We show up faithfully, but often tired, and sometimes wondering if our offering matters. But Easter reminds us that God specializes in bringing life out of sacrifice. What is given in love is never wasted!
If you are weary, your service matters. If you feel unseen, God sees. If you wonder whether one more appointment, one more shift, one more conversation makes a difference, it does. Faithfulness is rarely anything flashy, but it has eternal significance.
Because He gave everything, we are free to give.
And what you give - your time, your energy, your compassion - becomes part of a much larger story of redemption. You are participating in holy work. You are standing in the gap for the vulnerable. You are reflecting the heart of Christ and His love in tangible ways.
This April, as we celebrate resurrection life, may you be reminded that the love you and our pregnancy help volunteers pour out is not small. It reflects the pattern of the Gospel itself, a sacrifice that leads to life. May you feel deeply appreciated, not only by those you serve alongside, but by the God who called you to this work.
Thank you and your volunteers for your quiet yes, for your faithful presence, and for choosing love, again and again.
Resurrection hope fuels long-term faithfulness. And every hour given in love becomes part of a story far greater than any one moment, a story that carries the promise of new life.
Just As He Said
by Jor-El Godsey, President, Heartbeat International
“He is not here, for He has risen, just as He said.” – Matthew 28:6
These words were spoken by no less than an angel of the Lord to the women who came to visit the tomb of Jesus. Heaven’s messenger spoke of the most central reality of the Good News – that death was overcome. He is risen! Death had no power to hold Him,1 and He, through His grace, extends that same power to all who call upon His name.2
And it was just as He told them, and us.
So, what else did He say?
Well, He said that we’d suffer on account of Him.3 That the world would hate us because of Him.4 In fact, He promised that they would persecute us for His name’s sake.5
Ouch!
We suffer. We get persecuted. We’re hated.
But that’s not all He said.
He said that we would be blessed when others persecuted us because of the works of righteousness we do.6 Oh, and we definitely do works of righteousness. We stand in the gap for those who are contemplating a life or death decision. We actively oppose the deeds of darkness that attempt to obscure the light of truth, the power of God, and the promise of heaven.
He also said that we are more than conquerors.
Indeed, He promised that we would not be left alone or forsaken. We can trust He will be with us in every situation. Whether in the counseling room with a client, or in front of students in the classroom, He promises to be with us. That is true for the boardroom table or the banquet podium. His Spirit is with us at work for His good and perfect will, in us and through us.7
And He has empowered those who believe in Him to do the works He did, and even greater, He said.8
Think about it. Jesus showed works of mercy. We can do that also. Jesus moved people from death to life. In our way, changing a trajectory from hurtling to imminent death to the choice of life, and even life everlasting, follows that pattern. The part about “greater works” doesn’t seem possible when we’re talking about Jesus as God. We are not God, after all, which may come as a surprise to a leader or two we’ve known. But certainly, the greater works show how we, collectively, are reaching more people than Jesus did during His precious moments on earth. His Word flows through us into all our situations, empowering a greater reach than could have been imagined in the days Jesus walked the earth.
He said that He would take care of our needs.9
That’s important to relay to the woman who can’t see a way to support the child in her womb. We know that He will provide for His creation. But it’s equally as important to speak to our own hearts during a discouraging report from the finance committee or when wondering how we’ll find that key staff person we need so desperately.
Another thing Jesus said was that He gives us peace.10
Yes, that’s right. Peace, even knowing we’ll be persecuted. Peace when we are hated. Peace when we know that the temporal world is aligned against us, just as it was, and is, aligned against Him.
So, take heart.11 Because he also said, in that same scripture, “Do not let your heart be troubled; nor fearful.”
Yes, take heart.12
Jesus spoke these powerful words, too, when He said that He has “overcome the world.”12 We can take heart that He is with us, and for us, in this great work of pregnancy help, just as He said.
1 1 Corinthians 15:55-57
2 Romans 10:13
3 Romans 8:36
4 John 15:18
5 Matthew 10:22-24
6 Matthew 5:10-11
7 John 16:7
8 John 14:12
9 Matthew 6:26
10 John 14:27
11 Psalm 31:24
12 John 16:33
Honoring Years of Partnership and Dedicated Affiliates
Heartbeat International honored pregnancy help organizations celebrating milestone anniversaries at its 2026 Annual Pregnancy Help Conference. Heartbeat International Affiliation Coordinator Alaina Wood and Director of Affiliate Services Kathy Jerman delivered the awards to recipients for their recognized 25 and 50 years of service. Below are the heartfelt words spoken on behalf of all the Heartbeat International staff.
by Alaina Wood, Affiliation Coordinator
It has been such a blessing to see so many of you this week, and it is always a pleasure to put faces to the voices I’ve connected with by phone and email.
You may have heard from me when it’s time to renew your affiliation with Heartbeat, or I may have had the chance to speak with you when you’ve called looking for guidance or support.
It’s truly a joy to come alongside you and help connect you with the people and encouragement found through Heartbeat.
I have the honor of celebrating with you—organizations that have consistently shown up face to face with women, men, and families in their communities for decades. With determination, perseverance, and deep faith, these organizations have stood firm in their commitment to life for 25 and 50 years.
With compassion for each person created in God’s image, they have faithfully said yes to His calling day after day. They have prayed, dreamed, faced challenges, grown, and rejoiced—praising the Lord for His grace, guidance, and provision every step of the way.
In those face-to-face moments, they have shared the love of God with countless women, so that each one may know how fearfully and wonderfully made she is—and in turn, pass that love on to her child.
Because of this faithful, ongoing work, we celebrate the organizations that opened their doors in 2001, marking 25 years of faithful service to women and families:
Alliance for Life Missouri: Marsha Middleton
Options Pregnancy Center: Vikki Parker, Marsha Bailey
Smoky Mountain Pregnancy Care Center: Michelle Finnie, Karen Whitley, Krista Young, Pamela Bowen




We also honor those who opened their doors in 1976, marking an incredible 50 years of ministry and lasting legacy:
Guiding Star Wakota: Kenyatta Hardaway, Monica Elias
Solve Maternity Home: Peggy Kerwin



We’re so grateful for your faithfulness and deeply encouraged by the way God has sustained and guided your work over the years. It’s a privilege to see what He has done through you.
As we think about the calling each of you carry—whether you are just beginning, in the middle of the journey, or celebrating many years of ministry—we’re reminded of this promise from Thessalonians:
“May our Lord Jesus Christ himself and God our Father—who loved us and by His grace gives us eternal encouragement and good hope—encourage your hearts and strengthen you in every good work and word.” Selah
May He give you endurance, wisdom, and joy in the work you do each day—faithfully serving for 25 years, for 50 years, and many more to come.
A Couple of the Non-Negotiables of Imaging
by Tammy Stearns, MS, RDMS, RVT, RT(R), FSDMS, LAS
A Couple of the Non-Negotiables of Imaging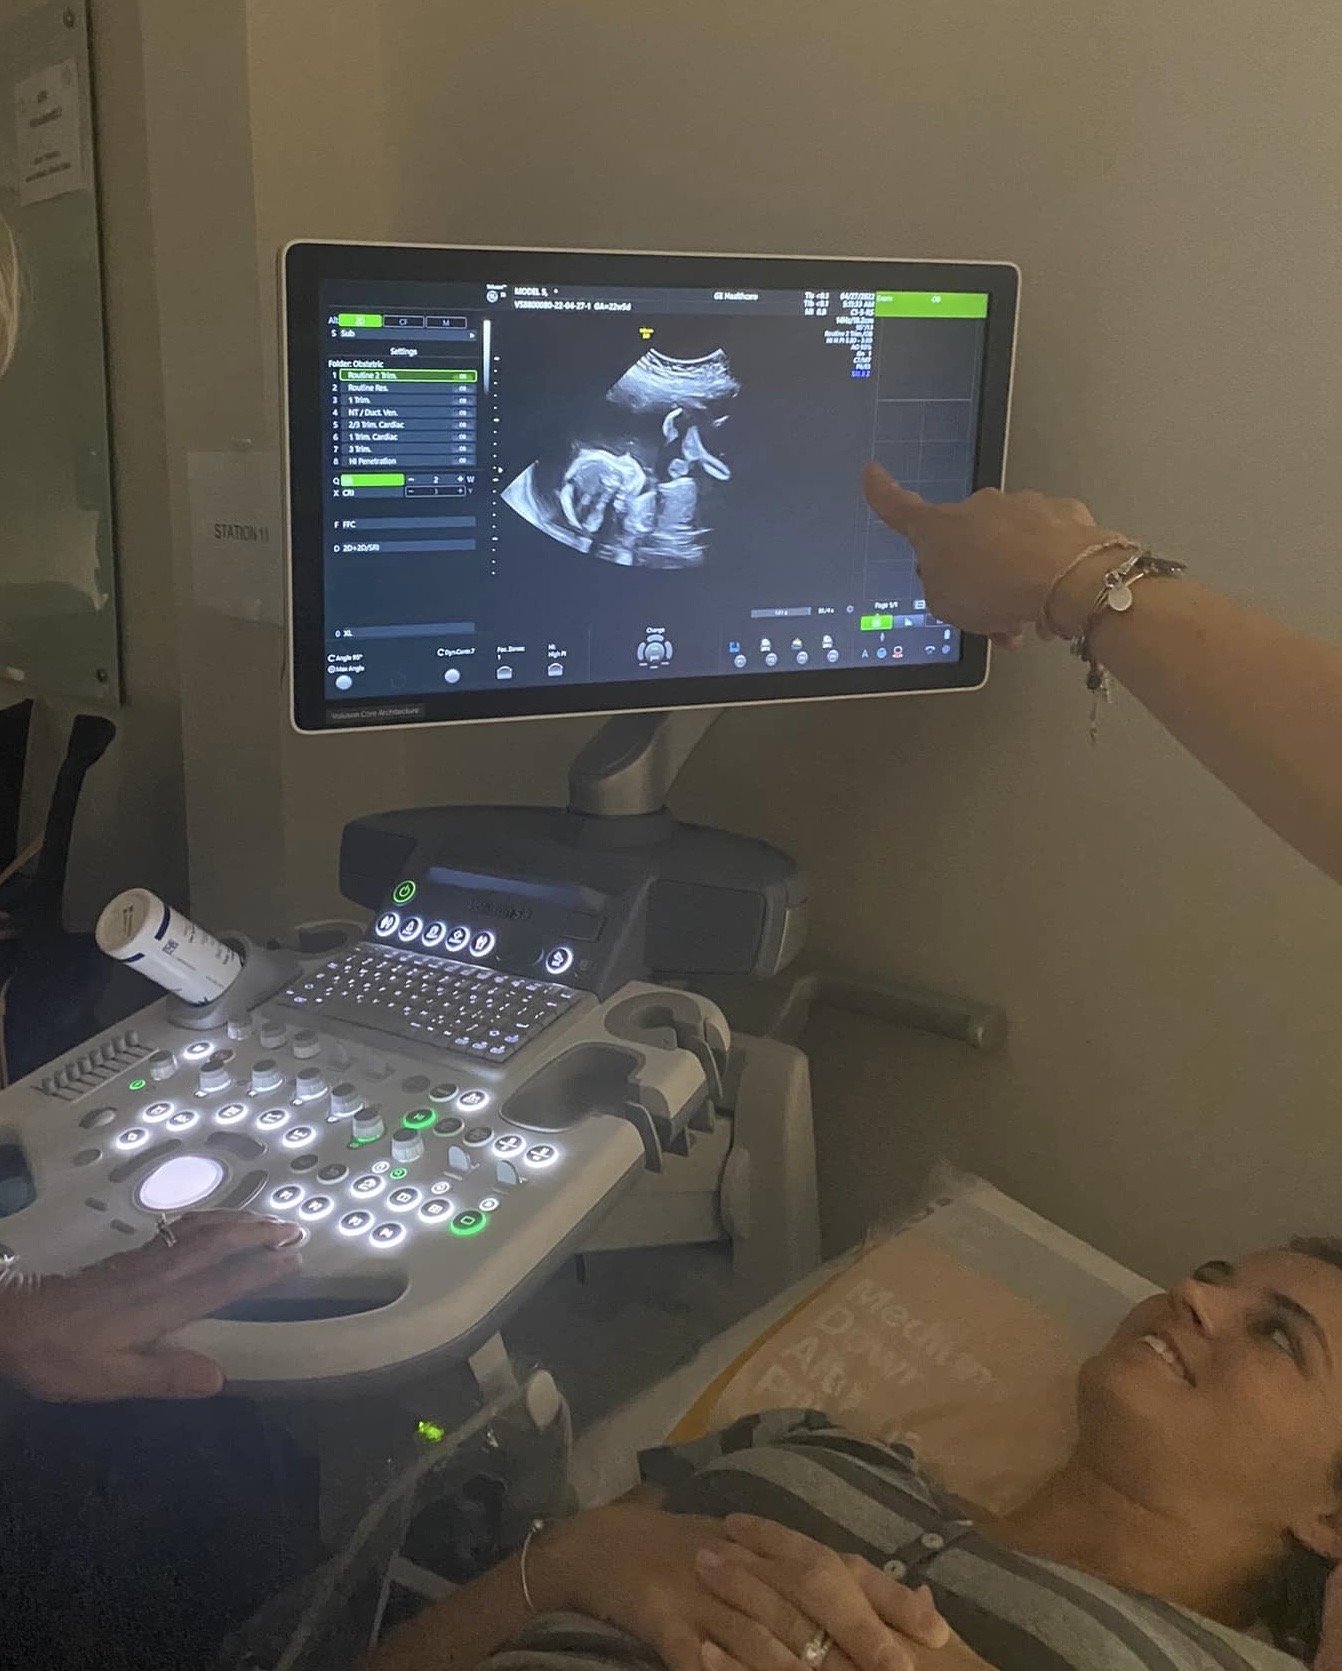
We’ve all had those situations. Due to the circumstances, can we quickly scan first? Typically, this situation occurs during a busy day at the Pregnancy Help Medical Clinic (PHMC) when the adrenaline is running high, with everyone feeling in a rush. Or, it has been such a slow day, week, or month that everyone finds themselves just ready to finish the day. Yet it is these very procedures and processes that help guide us, as imagers, to provide the mom with the most accurate information. These procedures and processes not only help ensure better quality of the scan, but they also protect us by ensuring that we have the information that we need to correctly understand her situation. Without the following non-negotiables, as imagers, we can give a lot of possibilities, but may also find ourselves in a position of not being able to adequately know what we are possibly seeing. As an imager, the extra time taken to ensure the presence of a positive pregnancy test and scanning with a full bladder is worth it.
Positive Pregnancy Test
“I know that we are supposed to have the pregnancy test before you scan, but could you look real quick, and we will do the test after? She did a test at home.”
It is a common procedure to have documentation of a positive pregnancy test prior to performing the ultrasound. Most PHMCs require the test to be performed on-site to document the results of the pregnancy test and do not rely on results from an at-home pregnancy test. This request to overlook doing the pregnancy test typically comes in one of two ways. Either the staff performing the tests is too busy, or there is concern that once the client empties her bladder, even the smallest amount, her bladder will be completely empty for the ultrasound.
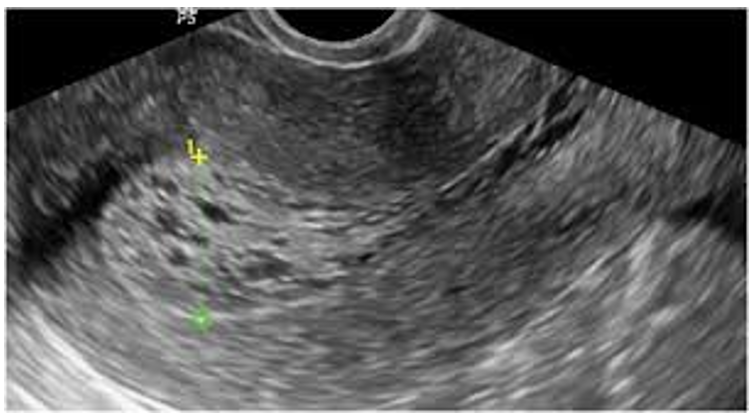
The challenge with ultrasound is that there are many “shades of gray”. Literally. There are many structures that image and look alike. There are many images that the understanding and final diagnosis of them will depend on whether the client has a positive pregnancy test or not. The next step in her care at the Pregnancy Help Medical Clinic will be determined by the results of her pregnancy test. For example, when a client shares she is confident in her dates and is 8 weeks per her LMP, with a cystic structure being visualized on the ovary with no gestational sac seen in the endometrial cavity in the uterus, we are looking at the possibility of an ectopic pregnancy if she also had a positive pregnancy test. If the pregnancy test is negative, then it is most likely a cyst on her ovary being imaged. One is an emergency. The other is not.

Another example could be a heterogenous appearance to a thickened endometrium that fills the entire endometrial cavity. The client claims she is 8 weeks by LMP. If the pregnancy test is positive, she could have had a missed miscarriage (a miscarriage that hasn’t been evacuated from the uterus) or a molar pregnancy. If the pregnancy test is negative, she could possibly have a missed miscarriage, as time has passed, the hormone level has dropped to insignificant levels. Another possibility is a thickened heterogenous endometrium due to hormonal issues or infection, not pregnancy-related.

Tips to help work through the request-
- Give her a cup to empty her bladder in. This gives her a reference on how much to empty her bladder and will keep her bladder full enough to scan.
- As soon as she receives the positive pregnancy test results, give her a couple of bottles of water to drink while her mentor is spending time with her prior to bringing her over to the ultrasound exam room.
Full Bladder
“She says that she can’t fill her bladder anymore, can’t we just scan with what we’ve got?”
“She says she’s full.”
“She’s in a hurry. Can’t you just scan?”
So many “workarounds” it seems regarding the full bladder, and yet, the full bladder is an important part of a transabdominal scan. The full bladder gives a structural landmark that helps orient the imager to the pelvic area. The full bladder pushes the bowel away from the area, allowing for better resolution. A full bladder will also provide what is referred to as a “sonic window”. The sound wave travels through the fluid-filled bladder unimpeded so that when it reaches the uterus, it has a greater intensity than the portion of the sound beam that has traveled through the adjacent soft tissue. This allows for better resolution. Ideally, the bladder should always extend past the fundus of the uterus. Always. The quality of images obtained with a full bladder as opposed to a partially full or completely empty bladder is worth the wait. A full bladder gives the imager a reference for the level of gain necessary for the exam. (This is true as long as the bladder is normal and anechoic)
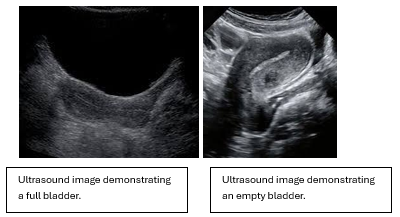
A possible soft tissue area adjacent to the uterus may appear as a mass without a full bladder. By filling the bladder, if the area is simply bowel, it may move or entirely disappear. The anteverted or anteflexed uterus will be stretched out lengthwise with a full bladder. With an empty bladder, it will remain in one area, making it difficult to thoroughly image the uterus. Sometimes images can be obtained with an empty or partially filled bladder, but too often the payoff of questionable quality images or remaining questions isn’t worth the time that was saved by not filling her bladder. The first question to be asked when evaluating a scan of the uterus will be why the bladder isn’t full. It is standard practice transabdominally.
Tips to help work through the request- (Same tips as above!)
- If she says her bladder is too full, let her empty her bladder a little bit. Give her a cup to empty her bladder, which gives her a reference on how much to empty her bladder, and will still keep her bladder full enough to scan.
- As soon as she receives the positive pregnancy test results, give her a couple of bottles of water to drink while her mentor is spending time with her, prior to bringing her over to the ultrasound exam room.
Fertility Awareness in Action
by Brooke Myrick BSN, RN, LAS & Kelly McCallister BSN, RN, LAS
This is the final article in a series of three bringing an emphasis of fertility awareness to equip and empower those in pregnancy help and ensure women understand their bodies to make informed choices in their healthcare.
Do our Pregnancy Help Medical Clinic (PHMC) clients track their cycles - completely?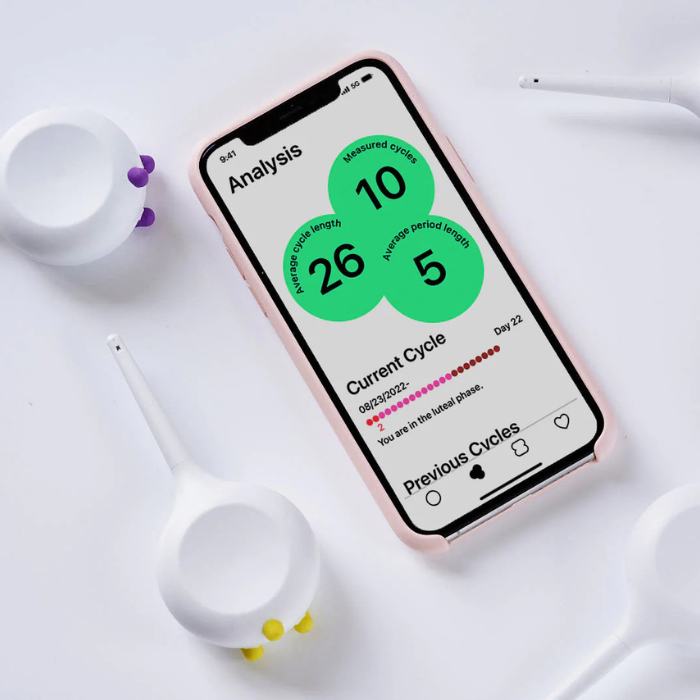
Most women today use an app on their phone to track their cycles, but are they able to ascertain the information necessary to understand how their bodies are functioning? A tracking app reflects data based on what is entered. If we are not able to provide the app with accurate observations, then the information it provides to us will be flawed. Most often, we only enter when our period starts and ends, but there is so much more our cycles encompass. Another consideration is that most tracking apps use algorithms based on a 28-day cycle to provide an estimation of ovulation. It is estimated that about 16% of women have a 28-day cycle and only about 13% ovulate on day 14, which is contrary to what has traditionally been taught. Where does that leave our Pregnancy Help clients?
Giving our clients the understanding and ability to learn the signs of her own fertility could be incredibly beneficial. Being attuned to identifying patterns is key to knowing what our body is communicating. Biomarkers are one such way that we can measure expected biological processes while also raising awareness when something might be amiss. Common fertility biomarkers include cervical mucus, basal body temperature, and hormone levels in urine and plasma. Of this list, cervical mucus is the most readily available to every woman.
What education can we provide our PHMC clients about their cycles?
During a cycle, a woman has a fertile window estimated to last about 6 days. Of course, this can vary from woman to woman and even cycle to cycle. Learning how to observe her biomarkers and what they mean can empower her to better identify her fertile period during her cycle. Whether her goal is to achieve or avoid pregnancy, this can prove useful over the entirety of her fertile years. According to an observational study published by the American Society for Reproductive Medicine, “when perceived accurately, more accurate clinical self-detection of the fertile window can be obtained by identification of peak mucus.” Does your client know the difference between fertile mucus and infertile mucus?
Fertile mucus is more estrogenic and conducive to providing an environment that supports sperm in reaching the egg upon ovulation. It is clear, lubricative in nature, and stretchy in consistency. The fertile mucus becomes increasingly copious towards ovulation. Infertile mucus is more progestogenic and creates a barrier for the cervix, making it unfavorable for sperm passage, and also provides protection from bacteria entering the cervix. It is opaque, dry, thick, and most often only observed in scant amounts. After ovulation has occurred, the corpus luteum produces progesterone, which helps support and protect a possible pregnancy. Progestogenic mucus may be observed during this time in the cycle. Progestogenic mucus may also be observed after menstruation due to the residual progesterone that was produced by the corpus luteum during the previous cycle.
Included below are the phases of a healthy cycle and basic events and observations of each:
- Menstrual phase- shedding of the uterine lining (bleeding)
- Follicular phase - signals follicle to prepare an egg (possible progestogenic mucus/ estrogenic mucus as ovulation approaches)
- Ovulatory phase- rapidly rising estrogen signals release of the egg (increasingly estrogenic mucus)
- Luteal phase- after ovulation; corpus luteum produces progesterone (progestogenic mucus)
What other factors could reveal more important information about her cycle health?
Other important factors to consider are symptoms that she notices throughout her cycle and any lifestyle factors that could affect her cycle. Symptoms are observations that signal what is happening in the body. Being aware of any symptoms such as acne, bloating, breast tenderness, fatigue, insomnia, irritability, pain, and weight changes (just to name a few) can help a woman better understand what her body is saying. Moreover, paying attention to when these occur during the cycle can be very revealing as well. When seeking professional help, these symptoms and the timing of their occurrence can help guide the medical professional as they care for a woman.
Lifestyle factors can also impact a woman’s cycle. Stress, diet, exercise, alcohol/tobacco/drug use, and medications or supplements taken can have an effect on a woman’s cycle. Noting these during her cycle, along with her other observations, can provide a more complete picture.
Hormones are responsible for many bodily processes. Working with your client to create healthy lifestyle goals can be beneficial for not only reproductive reasons but also for her overall health.
How can we practically apply education about fertility awareness?
Given all that has been shared in these three articles, here are three steps towards creating an action plan to apply fertility awareness education in your PHMC.
- Identify - Identifying those interested in learning more is a great place to start. Many clients in our pregnancy help medical clinics are seeking services that aim to educate and empower them. Find those interested in learning more about their bodies and how they function.
- Share - Provide educational materials for your clients that are easy to understand and communicate clearly how to make complete cycle observations. Using educational materials and fertility awareness apps that are informative and interactive can keep her engaged.
- Evaluate - As you share, continually assess her understanding, responsiveness, and your delivery of the education. Seek out further support or information regarding fertility awareness, as needed. There are a plethora of resources available to you as you collaborate with your client to assist her in understanding her cycles and when it is important to seek a higher level of care.
Maternity Housing Coalition | Leadership & Practice Series
The Space Between: Finding the Right Attachment in Maternity Housing Work
by Valerie Harkins, Executive Director, Maternity Housing Coalition
There is a tension that lives inside every good maternity home worker. It’s quiet most of the time, but it surfaces in the small moments. When a resident makes a choice you saw coming, you have to decide whether to step in or step back. When a young woman is circling the same painful pattern for the third time, and something in you wants desperately to grab the wheel. When a program rule feels cold in the face of a warm human story sitting right in front of you.
That tension doesn’t mean something is wrong with you. In fact, it might mean something is very right. The question is not whether you feel it; the question is how you manage it. Because that tension, held well, is precisely what makes great maternity housing work possible. Held poorly, in either direction, it becomes one of the most subtle and destructive forces in our field.
Let’s talk honestly about the two failure modes and the narrow, necessary road that runs between them.
The Problem of Over-Attachment
There is a kind of care that looks like love but functions like control. It’s warm, it’s well-intentioned, and it is quietly devastating to the people it intends to help.
Over-attached workers are not bad people. More often than not, they are the most passionate people on your team. They are the ones who stayed late, who cried in the car on the way home, who prayed hardest for the women in their care. But somewhere along the way, that passion crossed a line, and instead of walking with the resident through her journey, the worker began carrying the resident for her.
The clinical term for one dimension of this is toxic empathy, and it is worth understanding precisely. Healthy empathy is the capacity to feel alongside someone, to be genuinely moved by their pain, and to use that understanding to serve them better. Toxic empathy is what happens when that feeling becomes so consuming that the worker’s emotional state becomes entangled with the resident’s outcomes. At that point, the worker is no longer responding to the resident’s actual needs. She is responding to her own discomfort, her own need to see the resident succeed, to see the situation resolved, to relieve the ache of watching someone struggle.
The result is predictable: workers who over-correct. Who softens every hard edge. Who negotiate around natural consequences. Who quietly rearrange the environment so the resident never quite has to face the full weight of her own decisions.
And here is what that actually communicates to the resident, even when no words are spoken: I don’t believe you can handle this. I don’t trust you to grow from it. I need to protect you from yourself.
That message, however lovingly delivered, is profoundly disrespectful.
Consider this from a theological perspective. Christ did not remove free will to protect us from ourselves. He could have. Omnipotence affords that option. But He didn’t, because a life insulated from the consequences of one’s own choices is not a human life in any dignified sense. Free will is not a design flaw to be managed. It is the very mechanism through which transformation occurs. The prodigal son’s father did not chase him to the far country. He did not wire him money when the famine came. He let that young man sit in the mud with the pigs until something broke open inside him, and then he ran toward him. The father’s restraint was not indifference. It was the most profound form of respect he could offer.
When we over-shelter a resident from the consequences of her own choices, we are not being more loving than the Father. We are being less wise. We are removing the very friction that produces growth. We are, with all good intentions, robbing her of the lesson she came here to learn.
There is also a burnout dimension to this that we cannot afford to ignore. Workers who carry the weight of residents’ outcomes as if those outcomes belong to them will not last in this work. Compassion fatigue and secondary traumatic stress are well-documented in residential care settings, and over-attachment is one of their primary drivers. The worker who believes it is her job to save every woman who walks through the door will eventually be undone by the ones she couldn’t. Or worse, she will begin unconsciously choosing residents she believes are “save-able” and disengaging from those who are not. Neither outcome serves the mission.
The Problem of Over-Detachment
The opposite error is less emotionally dramatic but no less damaging. It wears a professional face. It follows every protocol. It produces clean paperwork and respects program boundaries. And it is hollow at its core.
Over-detached workers have learned, through exhaustion, through disappointment, through self-preservation, to create emotional distance between themselves and the residents they serve. They do their job. They complete the required check-ins, facilitate the required groups, and issue the required warnings. But somewhere in that process, the person sitting across from them has been replaced by a case.
This is the migration from serving the mission to serving the program. And it is more common than most of us want to admit.
A program, meaning its policies, schedules, rules, and procedures, is a tool. It is the scaffolding you build to create consistency and safety in a complex environment. A well-designed program is genuinely valuable. But scaffolding is not the building. It is not the reason you built the building. When workers begin treating the program as the point and the resident as the means of executing the program, something has gone spiritually wrong in the organization.
Here is the drift as it typically unfolds. An organization is founded on a burning sense of purpose. Someone saw a need, felt called, and built something to address it. In the early days, the mission is alive in the walls. Every decision, every exception, every conversation is filtered through the question: What does this woman need? As the organization grows, structure becomes necessary. Policies are written. Staff are hired. Job descriptions are formalized. This is not wrong; it is wise stewardship. But without intentional, ongoing cultivation of organizational culture, the structure slowly becomes the thing itself. Staff are evaluated on compliance with the program. Meetings are about program performance metrics. New staff are trained on the rules before they are formed in vision. The organization, imperceptibly and without anyone intending it, has begun to exist for itself.
C.S. Lewis described this kind of institutional decay as the corruption of something good rather than the creation of something evil. No one decided to stop caring about the mission. The mission simply got buried under the weight of operations.
And when the mission is buried, the residents feel it. They receive services, but they don’t receive presence. They are processed through a system, not welcomed into a community. They follow the rules because the rules are enforced, not because they are growing. And the moment they leave the program, the growth stops, because the growth was never really theirs to begin with. It belonged to the program.
We must remember: the soul of every resident who arrives at your door was directed there by God, not by your marketing budget or your referral network. That soul has a story and a dignity that no intake form can capture. To serve the mission of your organization is, ultimately, to steward the sacred trust of that person. When your organization begins to exist primarily for the purpose of being an organization, for sustaining its own programs, protecting its own budget, and perpetuating its own existence, it has ceased to be a ministry and become a bureaucracy. And bureaucracies, however well-funded and well-staffed, cannot do what you were built to do.
Engaged Presence Without Enmeshment
So what does it look like to get this right?
The goal is what some in the therapeutic community call engaged detachment, a posture that is fully present, genuinely invested, and emotionally alive, while remaining clear-eyed enough to stay out of the way when staying out of the way is the most caring thing you can do. It is not a halfway measure between caring and not caring. It is a third thing entirely, a more mature and more disciplined form of love.
Think of it as the difference between a guide and a rescuer. A rescuer is reactive. She cannot tolerate watching someone struggle, and her emotional system is organized around eliminating the struggle. A guide is intentional. She has been down the road before. She knows which falls are instructive and which are dangerous. She walks alongside, she points ahead, she celebrates hard-won progress, and she knows when to let someone sit with a difficult mile rather than carrying them through it. The guide is no less invested than the rescuer. She may actually love the traveler more, because her love is disciplined enough to serve the traveler’s actual growth rather than her own need for resolution.
In practical terms, this posture has several characteristics worth naming.
It makes room for failure. Maternity homes should be safe places to fail. Safety lives in the relationship and the environment, not in the absence of consequences. When a resident makes a poor financial decision, she should feel it. When she misses an appointment, that consequence should land on her, not be quietly absorbed by a well-meaning staff member. Remove the friction, and you remove the classroom.
It distinguishes between empathy and compassion. Empathy feels with someone. Compassion acts on their behalf, even when acting on their behalf means stepping back. A worker high in compassion can sit with a resident's pain without needing to fix it. She can say, this is hard, and I believe you have what it takes to get through it, and mean both parts equally.
It keeps the mission verbal and visible. The mission cannot be a sentence on the wall. It has to be the living reference point for every decision, present in staff meetings, in supervision, in the stories you tell about residents who have grown. Ask yourself: in your last three staff meetings, how much time was spent on program logistics versus talking about the actual people in your care?
It builds a program that bends without breaking. A healthy program is not static. The model that served your residents five years ago may not fit the women arriving today. Leaders attached to the mission rather than the program welcome that evolution. They expect it. A thoughtful adjustment each year is far healthier than clinging to a design because change feels risky or because the original model has become someone's professional identity.
It sustains the worker. Workers who care deeply but don't carry what isn't theirs to carry remain in this work. They don't burn out in two years. They don't grow the cynical shell that self-protection produces. They bring freshness to each resident because they were not depleted by the one before her. Understanding this balance is not a luxury for your team. It is a retention strategy and a quality-of-care strategy in one.
A Word to Leaders
If you are an executive director or program director reading this, I want to say something directly to you.
The culture of attachment in your organization is set by you. Not by your policies, by your example. The way you talk about residents in staff meetings, the way you respond when a resident fails, the way you frame success and loss for your team, all of it communicates what appropriate investment looks like. If you process residents as cases, your team will too. If you speak of them as souls, your team will too.
And when your program needs to change, when the data or the discernment or the direct feedback from residents tells you that something isn't working, be willing to name it and move. The most dangerous thing you can say in a mission-driven organization is: "This is how we've always done it." Because always doing it the same way is a declaration that the program matters more than the people. And you know better than that. That's why you're in this work.
A Closing Thought
We are a field full of people who chose this work on purpose. Nobody stumbles into maternity housing by accident. You are here because something called you here, a conviction, a story, a faith, a fire. That calling is real. Honor it by protecting it.
The women who come to your doors are not yours to save. They are God's to redeem. You are a part of that process, a vital, meaningful, irreplaceable part. But you are not the whole of it. Your role is to be present enough to love them well, and grounded enough in the mission that your love serves their growth rather than your comfort.
That is the narrow road. It is not easy to walk. But it is the one that leads somewhere.